


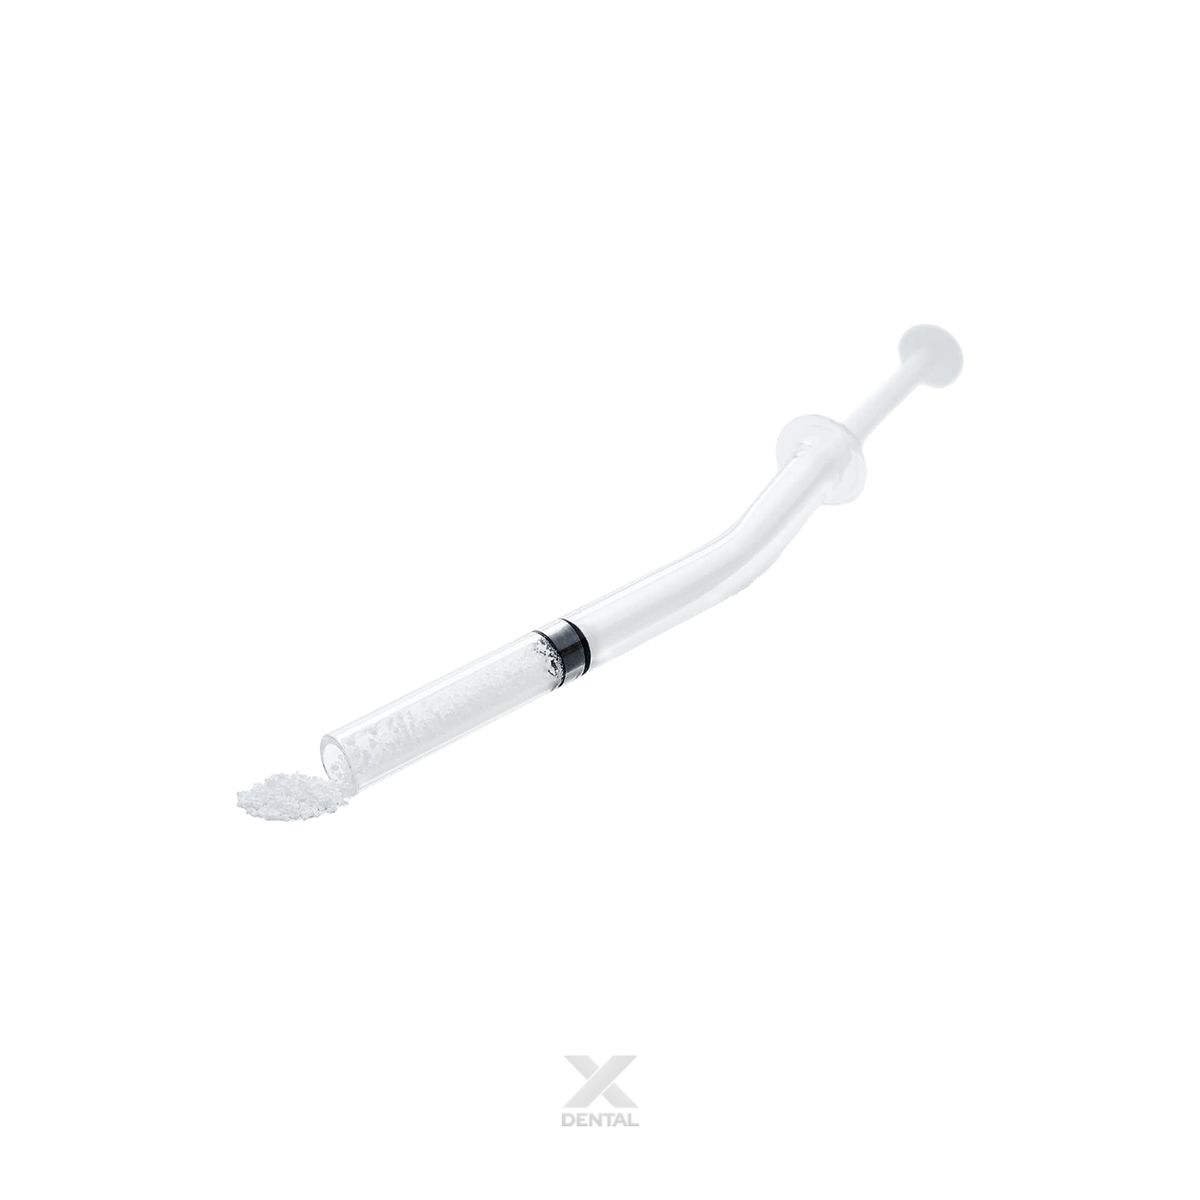

Synthetic Bone
Granules in a Syringe
RESORBA® Synthetic Bone is a fully synthetic bone graft substitute based on Micro-Macroporous Biphasic Calcium Phosphate (MBCP®) technology — a 60% Hydroxyapatite / 40% ß-Tricalcium Phosphate composition. Supplied as 0.5–1.0 mm granules pre-filled in a ready-to-use syringe, it combines the long-term volume stability of HA with the fast bioactivity of ß-TCP, providing an osteoconductive scaffold with a minimum 70% interconnected porosity for gradual replacement by the patient's own bone.
What clinicians are saying
Real-world feedback from implant and oral surgeons using RESORBA® Synthetic Bone in their practices.
"The pre-filled syringe is the detail that won me over for socket and smaller ridge cases — I can deliver the granules exactly where I want them without spilling half the graft on the tray. The 60/40 ratio holds volume the way I need it to through the healing period, and when I'm grafting outside the ridge contour I'll mix in a little autologous bone. Controlled, predictable, and clean to handle."
"What I appreciate about the biphasic composition is how the graft behaves over time — the ß-TCP fraction gets early bone activity going while the hydroxyapatite maintains the scaffold and volume. At re-entry the site looks well integrated with the surrounding bone rather than a block of unresorbed filler. For sinus and GBR work it's become a dependable option when a fully synthetic graft is preferred."
The biphasic MBCP® principle
Two calcium phosphates, each with a distinct role — engineered to work together for a graft that is gradually replaced by living bone.
Chemically similar to the mineral phase of natural bone, HA is biocompatible and slow-resorbing. It grants long-term volume stability and a stable scaffold for cell adhesion.
More soluble and with fast bio-reactivity, the ß-TCP fraction enhances the ingrowth of pluripotent regenerative cells and triggers new bone formation.
Released calcium and phosphate ions stimulate osteoid formation by migrating osteoblasts — so the biphasic graft is gradually replaced by the patient's own bone.
When to use RESORBA® Synthetic Bone
A versatile synthetic graft across the full range of oral bone augmentation procedures — used alone, with a barrier membrane, or as an autograft extender.
Structure, healing & clinical track record
Micro-macroporous architecture and histological findings that show gradual graft replacement by vital bone, supported by a long clinical record.
① Micro-macroporous structure for maximum permeability

RESORBA® Synthetic Bone vs. Human Bone (SEM)

Interconnected Macropores (SEM)
- Minimum 70% global porosity — comparable to cancellous bone, colonised by the body's own cells
- Interconnected macropores promote biological infiltration and cellular colonisation by osteoblasts and osteoclasts
- Micropores — the intercrystalline spaces where dissolution and recrystallisation occur — support resorption and remodelling
- High specific surface area (SSA) for maximum permeability
② New bone formation & gradual replacement

6 months post-op — sinus augmentation (×100)

10 months post-op — sinus augmentation (×400)
- At 6 months, MBCP® particles are embedded in newly formed bone, with marrow space filled by loose connective tissue and abundant blood vessels
- At 10 months, grafted material and vital bone are in close contact, with visible osteocytes and a clear reversal line in the newly formed bone
- Over the healing period, new bone increases as the graft gradually resorbs — a balance of resorption and bone ingrowth
③ A proven clinical track record
- Human sinus-lift biopsies of the same MBCP® 60/40, 0.5–1.0 mm granules: micro-CT showed roughly 53% of the granules resorbed and about 22% newly formed bone intimately associated with the granules within the first 6 months, with bone ingrowth sufficient to support dental implants at 6–8 months (Mailhac & Daculsi, 2008)
- Human maxillary sinus augmentation: MBCP® performed predictably as a sinus-floor grafting material — alone or combined with other grafts — in the posterior maxilla (Lee et al., 2008)
- Backed by more than 30 years of clinical experience and over 1 million units manufactured
Real-world clinical outcome
Case with kind permission of Juraj Brozović (DMD, PhD, Asst. Professor, Specialist in Oral Surgery) — demonstrating RESORBA® Synthetic Bone 0.5–1.0 mm granules in an augmentation procedure.
Fenestration Management after Apicectomy
Bone loss following apicectomy, grafted with RESORBA® Synthetic Bone (0.5–1.0 mm granules) — stable healing at 6-month follow-up

Visible bone loss after apicectomy

Granules (0.5–1.0 mm) inserted into the defect

Coverage with a resorbable collagen membrane

Post-op CT at 6-month follow-up
This product
RESORBA® Synthetic Bone, 60% HA / 40% ß-TCP mix, supplied as granules in a ready-to-use syringe.

| Composition | Particle Size | Content / Box |
|---|---|---|
| 60% HA / 40% ß-TCP (MBCP®) | 0.5 – 1.0 mm | 1 syringe, 0.5 cc |
Technical specifications
| Device type | Resorbable synthetic bone graft substitute (bone void filler) |
| Technology | Micro-Macroporous Biphasic Calcium Phosphate (MBCP®) |
| Composition | 60% Hydroxyapatite (HA) / 40% ß-Tricalcium Phosphate (ß-TCP) |
| Format | Granules pre-filled in a ready-to-use syringe |
| Global porosity | Minimum 70% — interconnected macro- and micropores |
| Structure | Similar to cancellous bone |
| Resorption | Gradual; total resorption time varies with defect size, location, surgical protocol, and patient health status |
| Shelf life | 5 years |
| Medical device class | Class III (CE — Notified body TÜV SÜD Product Service GmbH, n° 0123) |
| Brand | RESORBA® (Advanced Medical Solutions) |
| Manufacturer | Biomatlante SA — Vigneux de Bretagne, France |
| Origin | Made in France |
Getting the most from RESORBA® Synthetic Bone
Practical guidance for predictable augmentation outcomes.